Short answer
Cleaning your emergency vehicles works when three things happen in order. First, the organic soil is physically removed. Second, a registered disinfectant stays wet on every surface for the time on its label. Third, the product suits the vinyl, plastics, and electronics it touches. Germs spread quickly through a patient compartment. So the science is about reaching the hidden touch points, not just the ones you can see.
Why is a patient compartment so hard to get truly clean?
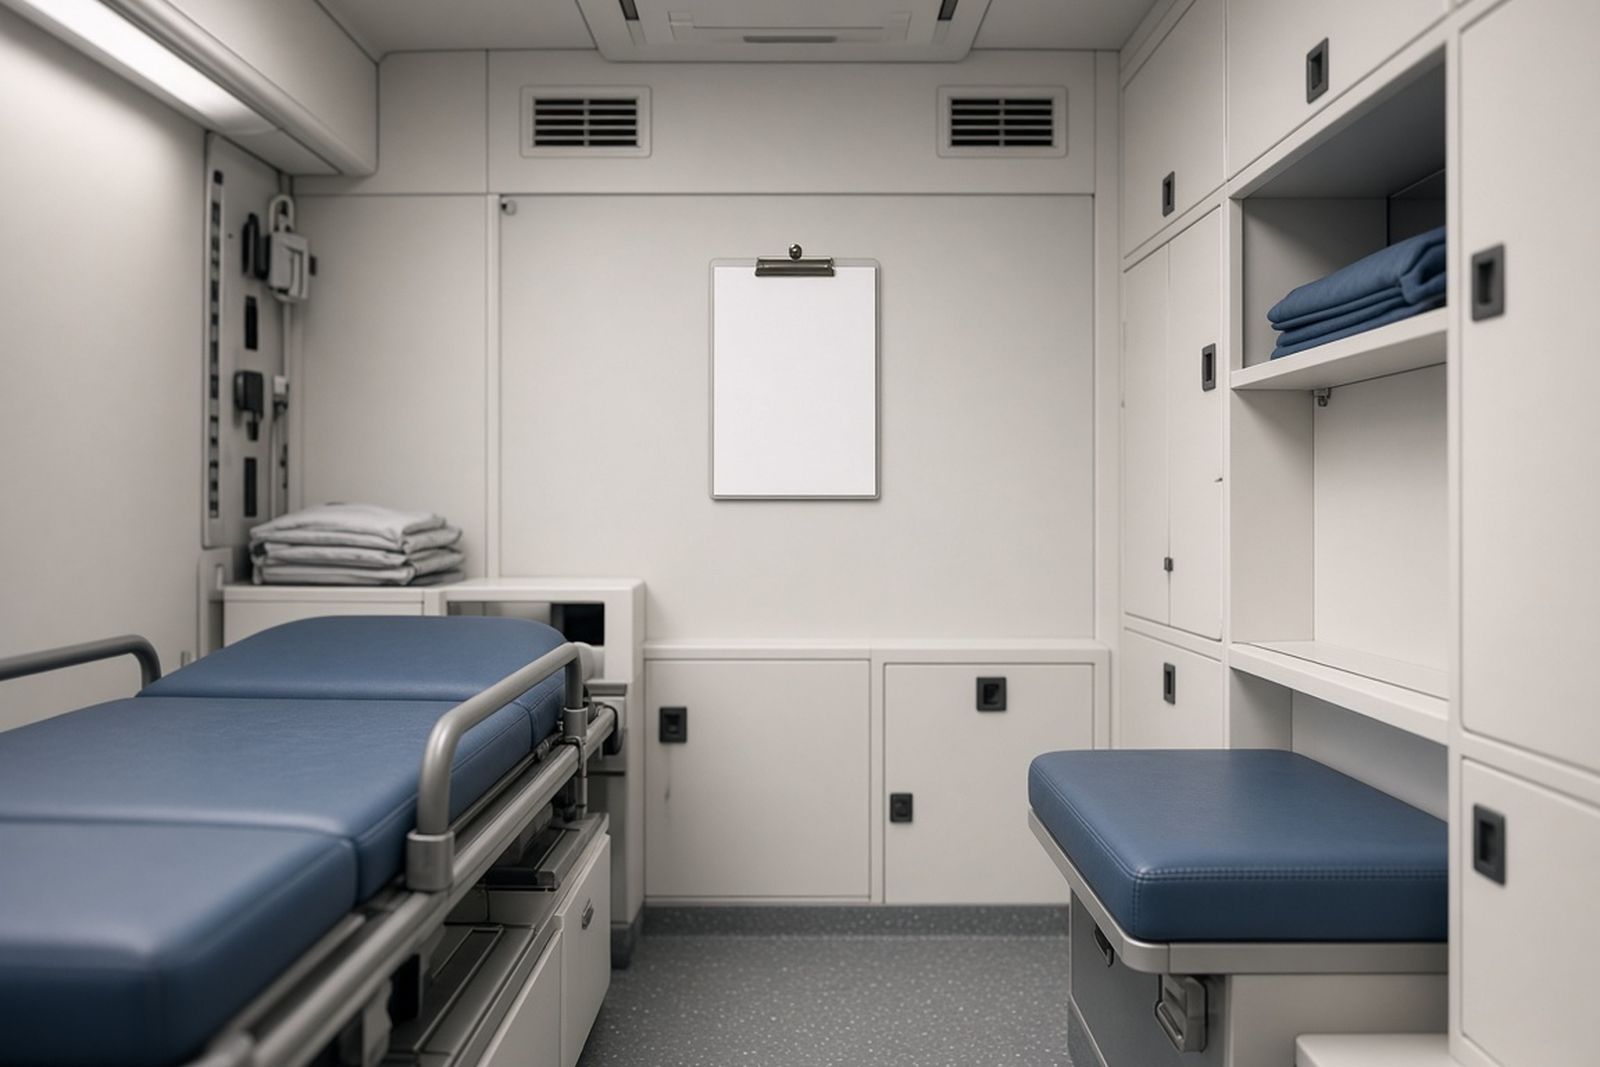
An ambulance box is a small room packed with seams, straps, hinges, and textured plastics. Each of those gives microbes a place to settle where a cloth does not easily reach. Add shaking, swings in temperature, and constant hand contact. You get a space that behaves very differently from a hospital room.
Your crews also work fast. Gloved hands move from the patient to the monitor to the cabinet latch to the radio in seconds. Each touch can carry material to a new surface. Researchers have tested this directly. In a 2015 field experiment published by Valdez and colleagues, a harmless tracer placed on seeded surfaces spread to 27 of 48 other sampled sites during a simulated response.
That finding explains why fleet managers talk about mapping every touch point and not just wiping the stretcher. The mess you cannot see usually matters more than the spill you can.
Cleaning comes before disinfection
Cleaning and disinfecting are separate steps with separate jobs. Cleaning uses detergent, scrubbing, and rinsing to lift blood, mucus, vomit, and dirt off a surface. Disinfection uses a registered chemical to kill the germs that remain.
Skipping the first step weakens the second. Proteins in blood and other body fluids can bind to some active ingredients or cancel them out. A thin film of residue can shield the germs under it. A disinfectant sprayed over dried fluid in a floor track may never touch the microbes sitting below.
This is also why many vehicle programs favor pre-wetted wipes or a two-bucket method for heavily soiled units. The first pass removes most of the soil. The second pass delivers the active ingredient to a surface that can take it.
The amount of soil also changes how much product you need. A wipe already soaked with blood or vomit stops delivering fresh product and starts spreading residue. Swap wipes often. Work from the least soiled areas toward the most soiled. That keeps the product doing its job across your whole compartment.
Wet time in a fleet on the move
Every registered disinfectant has a label that says how long the surface must stay visibly wet to kill what it claims. This is called contact time. The number comes from tests against certain germs under certain conditions. If the surface dries early, the label claim no longer holds.
Vehicles make that harder than a building does. A compartment warmed by the sun or the heater can dry a wet surface quickly. The pressure to get your unit back in service tempts crews to wipe and go. Upright surfaces and smooth plastics shed liquid faster than flat ones.
Good programs solve this with process, not hope. They choose products whose contact times fit how they work. They apply product again when surfaces dry early. And they treat the full wet time as a firm gate before a unit is marked available.
How your vehicle's materials change the chemistry
Ambulance interiors mix vinyl seats, clear hard plastic, aluminum, stainless steel, rubber seals, and delicate electronics. Each reacts in its own way to oxidizers, alcohols, quaternary ammonium compounds, and chlorine. A product that works well on a steel rail can cloud a monitor screen. It can crack a plastic housing over months of use.
Damage to materials is not only about looks. Cracked vinyl and crazed plastic form tiny holes and splits that hold soil and resist later cleaning. So a harsh product can make your future decon harder. Equipment makers publish guidance on which products are safe for their devices. That guidance should shape what you buy.
Soft items add another layer. Cot straps, seat belts, and cloth restraints soak up fluids. Many agencies launder or replace them and do not try to disinfect fabric in place.
Do spores and resistant organisms change the chemistry?
Yes. This is where choosing a product stops being a buying decision and becomes a medical one. Germs differ in how hard they are to kill. Viruses with a fatty outer coat tend to give way to most registered disinfectants. Viruses without that coat, such as norovirus, are tougher. Bacterial spores, such as those made by C. difficile, are among the hardest targets of all.
A general-purpose quaternary ammonium wipe may carry strong claims against many bacteria and viruses. Yet it may have no claim at all against spores. Say your crew carries a patient with known or suspected C. difficile. The product on your shelf may not be the right one for that deep clean. Products that kill spores are often based on chlorine or peracetic acid. They usually need longer contact times and are harsher on materials.
Bacteria that resist many drugs, such as MRSA, are a different issue. Resisting antibiotics does not generally mean resisting disinfectants. So a registered product used correctly will usually still work. The risk with these germs is that they last and spread. That brings you back to coverage and technique, not a special chemical.
The practical approach is to keep a small decision table in your station. Routine calls use the standard product. Certain flagged exposures set off a named alternative, with its own contact time and its own cautions for materials.
Research on service-ready units
Studies of real fleets suggest that a unit marked ready is not always as clean as its crew believes. In a 2026 study, Schaps and colleagues reported that 60% of ambulances labelled service-ready had at least one targeted pathogen on sampled surfaces.
Earlier work points the same way. Noh and colleagues sampled 13 ambulances in Seoul in 2011 and found bacteria in 214 of 429 samples, though they noted most were environmental flora and that detection does not mean infection. Environmental flora are everyday bacteria found in the surroundings.
The practical lesson is not alarm. It is modesty about what you can know by looking. Your eyes cannot confirm that a surface is free of microbes. That is why some agencies add checks from time to time. They use glow-in-the-dark marker checks or a quick swab test that shows leftover organic residue (it does not detect germs). These show whether the routine is reaching the surfaces it is meant to reach.
Where germs hide inside a unit
The high-risk list looks much the same in most ambulances. It includes surfaces people touch without thinking and places where fluid can pool or soak along a seam.
Police and fire vehicles have their own versions. In patrol cars, look at prisoner-seat seams and partitions. In engines, look at air-pack seats, cab grab handles, and medical bags.
- Cot rails, mattress seams, and the cot mounting track in the floor
- Cabinet latches, drawer pulls, and the edges of sliding doors
- Monitor cables, blood pressure cuffs, and fingertip oxygen sensor clips
- Suction units, oxygen regulators, and the bodies of cylinders
- Grab handles, ceiling rails, and seat belt buckles
- Radio handsets, keyboards, and tablet mounts
- Floor seams, drain channels, and the step well at the rear doors
- Air intakes and the areas right around them
Illustration: a unit that fails a fluorescent audit
Here is an illustration of a common result. A county agency runs a check every quarter using a gel that cannot be seen in normal light but glows under UV light. A supervisor dots the gel on 20 surfaces in a unit. The crew does its standard clean between calls. Afterward, the supervisor checks the dots with a UV light.
The stretcher, the bench seat, and the countertop come back clean. Four dots remain. They are on the suction canister bracket, the underside of the cot rail, the cabinet latch nearest the airway seat, and the radio handset. None of those surfaces looked dirty. The crew had no reason to skip them. They simply were not part of the habit.
The agency responds by rewriting its wipe order as a route that runs top to bottom and clean to dirty. It adds the missed surfaces to a laminated card and tests again a month later. The point is not to blame the crew. It is to make the unseen part of the job visible.
Putting the science into your program
Build your process around what the evidence shows. Remove soil first. Choose registered products whose label claims match the germs you worry about. Their contact times should be ones your crews can really meet. Before you switch products, confirm with the makers of your vehicles and equipment that the new ones are safe for your materials.
Measure. Do not assume. A simple checking tool tells you far more than a checklist signed at the end of a shift. Some exposures are heavy, such as major bleeding, a known resistant germ, or a crash that scattered supplies. For those, think about a full deep clean or an outside company with experience in vehicles.
Last, treat fogging, UV devices, and charged-spray machines as add-ons, not replacements. They can reach air ducts and awkward shapes. But none of them lifts dried fluid off a cot rail. Hand cleaning still has to come first. A device only earns its place when you use it on surfaces already free of soil you can see.
Before you settle on a written protocol, ask for input. Talk to your medical director and your state EMS office. Talk to the makers of your vehicles and equipment too.
Sources
- Valdez et al. — Spread of infectious microbes during emergency medical response
- Schaps et al. — Service Ready Ambulance Surfaces and Emergency Medical Services Clinicians are Routinely Contaminated
- Noh et al. — Risk Stratification-based Surveillance of Bacterial Contamination in Metropolitan Ambulances