Short answer
A written work plan that holds up later names the event that set it off. It splits your unit into zones and lists every surface and piece of equipment to be cleaned. It matches products to materials and says how waste is handled. It also says how the unit will be checked and returned to service. The made-up example below shows how you and a contractor might build that plan together.
A work order vs a plan that holds up
A work order says clean medic 12. A written work plan, which crews often call the work plan, says much more. It says what happened and which parts of medic 12 were affected. It says what was done to each part, with what products, and by whom. It says how the unit was judged ready to go back in service. Months later, your medical director, an insurer, an auditor, or a crew member with an exposure question can still review it.
A written plan protects everyone. The contractor can show it did what it agreed to do. Your agency can show it made sound choices with the facts it had. Your crews can see that the unit they are about to work in was handled with care.
Everything in the example that follows is invented for teaching. The agency, the call, and the unit are fictional. Nothing here describes a legal requirement. The aim is to show a planning process you can adapt.
A good plan also slows people down at the right moment. After a hard call, the urge is to get the unit back in service as fast as you can. Stopping for fifteen minutes to write down what happened and what needs doing usually saves time overall. The contractor shows up with the right products. Nobody has to redo work that was missed.
The made-up call: a transport with heavy bleeding
The agency in this example is a suburban fire-based EMS service. One of its advanced life support ambulances goes to a car crash. It carries a patient with serious injuries and heavy bleeding. On the way, the crew manages the airway, starts an IV line, and does a procedure that produces more blood.
At the hospital, the patient is handed off. The crew sees blood on the stretcher, the floor, the wall of controls and supplies beside the patient, and the side bench. There is blood on a suction canister that tipped and on the rear step. A heart monitor cable is clearly soiled. One crew member reports a splash on the forearm above the glove line.
The crew does a first rough cleanup at the hospital bay. They bag linens and secure needles. Then they drive the unit back to the station, out of service. The battalion's EMS officer decides the unit needs a deep clean by the agency's contracted vendor before it goes back on the road.
The crew member with the splash is sent through the agency's exposure process right away. That step is separate from the work plan for the vehicle. But it is noted in the event record, because it shows the event carried a real risk of exposure.
First questions that shaped the plan
Before the contractor arrives, the EMS officer and the vendor's project lead have a short phone call. The aim is to gather facts. It is not to guess at a price or a timeline.
The answers go into a brief note that becomes the first page of the file. You could ask the same questions.
- What kind of call was it, and was any infection concern flagged beyond the usual risk from blood?
- Which areas of the unit had a mess you could see, and what rough cleanup has been done?
- Were any doors or compartments open during the call that a splash may have reached?
- Which pieces of equipment stayed on board, and which went into the hospital?
- What are the stretcher mattress, bench cushions, and flooring made of, and are any damaged?
- Which disinfectants does your agency approve now, and do the makers of the monitor and other electronics set any limits?
- Where will the work take place, and does that spot have suitable drains and fresh air?
Dividing the unit into five zones
Zones keep your plan specific. They also help you avoid a common mistake. That mistake is scrubbing the obvious areas with care while giving the cab and outside compartments a hurried wipe.
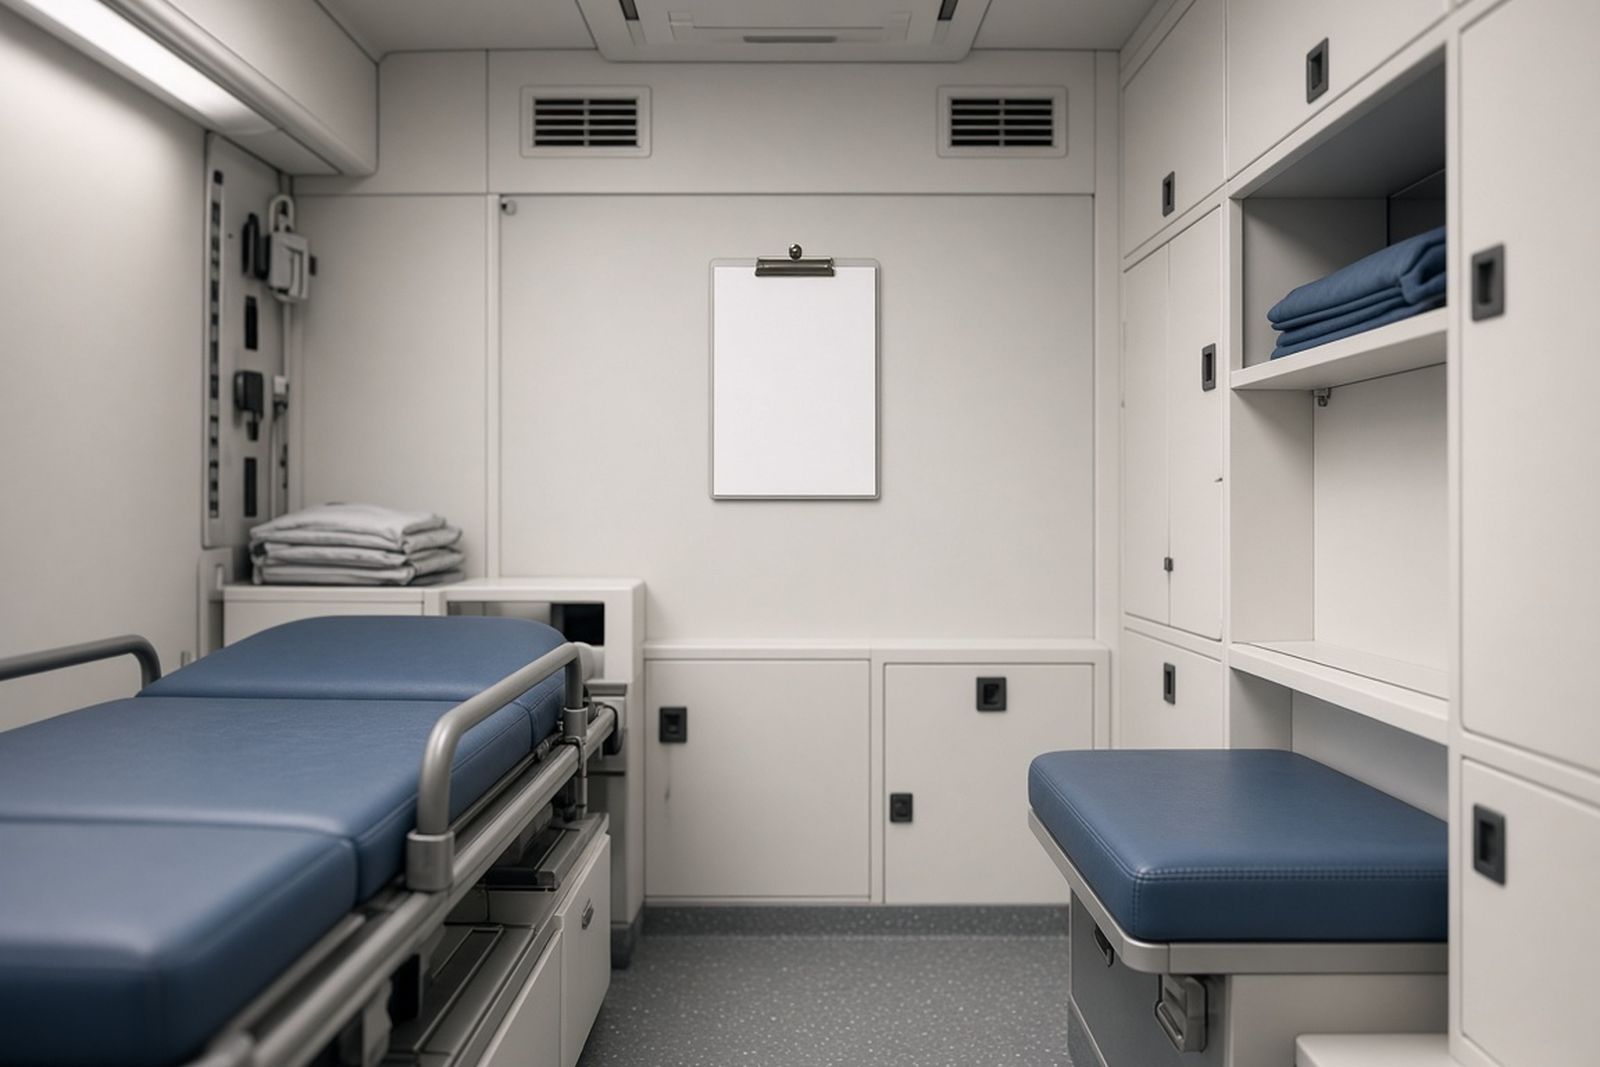
In this example, the project lead suggests five zones. Zone A is the patient compartment floor, stretcher mount, and rear step. Zone B is the wall of controls and supplies, the cabinets, and the ceiling. Zone C is the side bench, captain's chair, and seatbelts. Zone D is the cab, with the steering wheel, radio, dash computer, and door handles. It is included because crew members drove back with gloves off after the call. Zone E is portable equipment: stretcher, monitor and cables, suction unit, and airway bag.
Each zone gets its own line in the plan, with the surfaces listed and the method named. Suppose Zone D turns out to have no mess anyone can see. The plan still calls for disinfecting the spots hands touch most there. Hands carry material from one compartment to another.
How did product and material choices get written down?
The inside of an ambulance holds vinyl, coated fabrics, clear hard plastic, aluminum, rubber, and delicate electronics. A product that works well on your floor may harm a monitor screen. It may crack a plastic housing over time.
Research on plastics makes the point. In chemical resistance testing reported by Jennings and colleagues in 2024, products above pH 8 accounted for 74% of failures in the experiment. That study was not about ambulances in particular. But it shows why your plan should name each product and where it will be used.
In this made-up case, the plan lists three products. There is a detergent to remove soil. There is the agency's approved registered disinfectant for most hard surfaces. And there is the wipe the monitor's maker approves for the device and cables. The plan gives the label time each product must stay wet. It adds a note that surfaces must look wet for that full time.
The stretcher mattress has a torn seam, so fluid may have soaked into the foam. The plan calls for the mattress to be removed and replaced, not cleaned. The replacement is to be recorded with its part number.
Waste and water
Waste planning is often left for last. Do not let that happen in your plan. The plan in this example covers soaked linens, the damaged mattress, used wipes, and protective gear. All of it will be packed as regulated medical waste under the agency's contract with its waste hauler. Needles found during cleaning go into a hard container.
The work takes place in a station bay with a floor drain. The plan notes that the vendor will use very little water. It will rely on wipes and on spraying and wiping. No hose will be used inside the patient compartment. Any rinse water from cleaning removable equipment will be collected. It will go down a sanitary sewer connection that station maintenance has confirmed.
Your state medical waste program is usually housed in the environmental or health agency. It sets how regulated medical waste must be packed, stored, and moved where you operate. Confirm those details before you write them into a plan.
Deciding how to check the work before it starts
If your plan does not say how success will be judged, you invite arguments later. In this example, the EMS officer and project lead agree on three layers of checks before any cleaning begins.
First comes a look at every zone under strong portable light. That includes stretcher parts, seatbelt buckles, and cabinet tracks. Second is a record of each product used, its lot number where there is one, and how long it stayed wet in each zone. Third is a quick swab test on a fixed list of spots that hands touch most. The readings are compared with the agency's own baseline. Any spot above its trigger number gets cleaned again.
The plan says plainly that this swab test measures leftover organic residue, not germs. The checks support the work. They do not prove that no infectious germs remain.
When a check fails
They also agree on what happens if a check fails. A spot above its trigger is cleaned again and tested again. The second reading is written next to the first one and does not replace it. If the same zone fails twice, the project lead and the officer look together for the cause. It could be technique, the product, or a damaged surface. If you write this down ahead of time, you remove any pull to quietly swab again until a number looks good.
What went into the return-to-service record?
When the work is done and the checks are finished, the EMS officer walks the unit with the vendor's lead. Together they confirm three things. Each zone has been dealt with. Equipment has been put back correctly. Nothing was damaged during cleaning.
The final file holds the first-call note and the zoned plan. It holds photos from before and after, and the product and wet-time records. It holds the swab results with any retests, the waste paperwork, and the mattress replacement record. Both leads sign it. The unit goes back in service only after the officer signs.
Why go to this length? Routine cleaning under time pressure tends to miss the same places. Those are seams, latches, buckles, and equipment that nobody thinks of as dirty. A written, zone-by-zone approach is one way to lower the chance that your busy crew misses them again.
Lessons to take back to your agency
You do not need a fancy system to build a strong plan. You need a short first call, a plan split into zones, and a product list matched to materials. You need a waste plan, agreed checks, and a signed final file.
Think about making a template for your fleet. Match the zones to your unit layouts and fill in your approved products ahead of time. When a call with a heavy mess happens, your officer on duty can fill in the facts. Nobody has to start from a blank page.
Review your finished plans from time to time. Maybe the same surfaces keep needing a second clean. Maybe the same equipment keeps getting damaged by the wrong product. The pattern will show up in your files long before it shows up as an infection concern or a costly repair.