Short answer
Expect a short talk about the exposure first. Then a team takes your unit out of service, removes the equipment and soft items, and searches for needles. They clean every surface from top to bottom and apply a registered disinfectant for the full time on its label. Soft items are cleaned or replaced. Equipment is disinfected on its own, and the unit is restocked. It ends with a written record and a formal return to service.
What will the company ask before the unit arrives?
A professional decontamination, or decon, starts with a few questions. Expect to be asked what type of unit it is and what happened on the call. The company will ask whether a certain germ is known or suspected, whether needles were involved, and whether the unit was in a crash.
The company will also want to know what your agency expects to get back in the unit. It will ask which soft items and equipment you want replaced and which cleaned. It will ask whether any items should go to your own equipment officer. If your agency has a standard decon checklist, send it. Then the company can follow your format.
Share only the medical details needed to choose products and protective gear. You do not need to name the patient. Your privacy officer may have guidance on what you can share.
Tell the company where the decon will happen. A station bay with drains, light, and fresh air is best. A parking lot may limit which products and methods can be used.
Taking the unit out of service and getting it ready
Take the unit out of service with dispatch before decon begins. Then no one sends it to a call partway through. The crew that brought it in usually takes out their personal gear and anything that belongs to them.
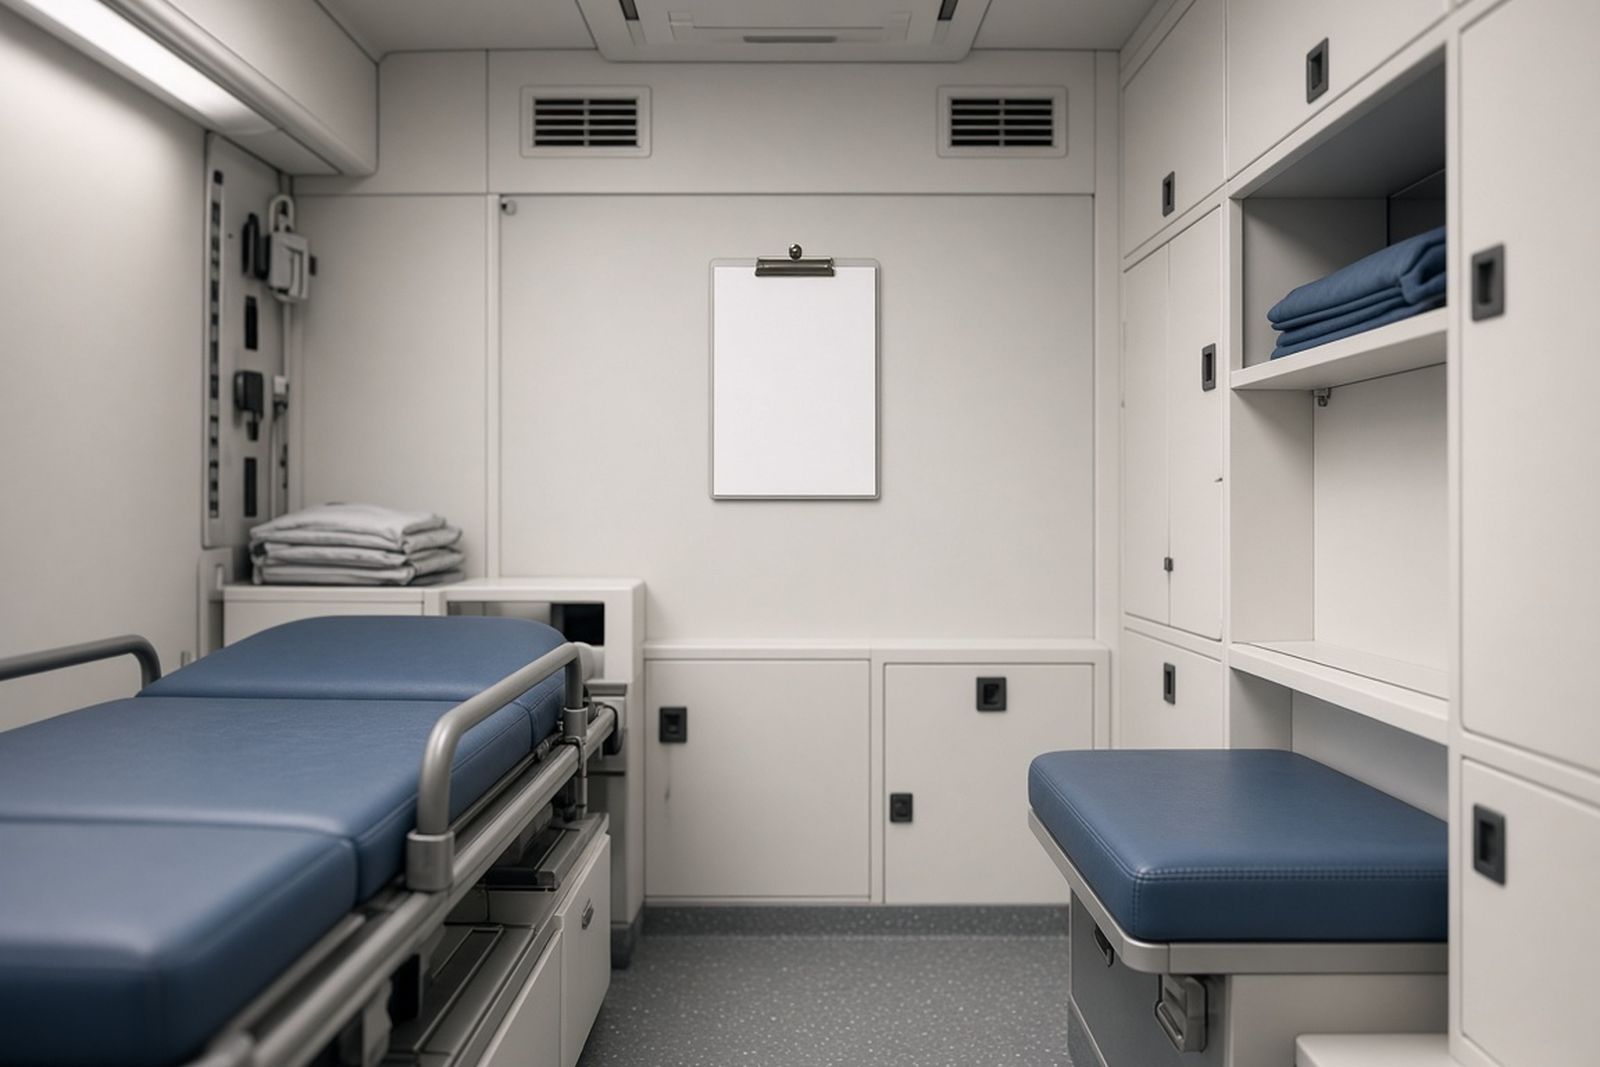
The decon team then empties the compartment. Portable equipment comes out to be cleaned on its own. That includes monitors, suction units, jump bags, and stair chairs. Soft items such as cot mattresses, straps, and linens are pulled and checked. Supplies that were opened or may be soiled are thrown out as your policy directs.
A careful search for needles and other sharp items comes next. Technicians check under the cot, along floor seams, behind seat cushions, inside cabinet tracks, and in door pockets. They do this before they put their hands anywhere they cannot see.
Expect the company to photograph the compartment before anything is moved. Those pictures help if questions come up later about what was soiled or which items were thrown out.
Cleaning order: top to bottom, clean to dirty
A good team works from top to bottom and from cleaner areas to dirtier ones. That way the mess does not drip or get dragged back onto finished surfaces. The heavy soil comes off first, since disinfectants work poorly on surfaces still covered with organic material.
Every hard surface is then cleaned, rinsed if the product calls for it, and treated with a registered disinfectant. The surface must look wet for the full time on the label. On walls and ceilings, that may mean applying the product again.
- Ceiling, light covers, grab rails, and IV hooks
- Upper cabinets, doors, and handles
- Walls, countertops, and the work area beside the patient
- Seats, seat belts, and headrests
- Cot mount, the bracket that holds the head of the cot, and the floor fastening points
- Floor, floor seams, and the step well
- Cab controls, radio, and steering wheel, if the crew worked in the cab after touching the patient
Why is contact time such a sticking point?
Contact time is how long the disinfectant must stay wet on a surface. In a busy system, the pressure to get a unit back on the road never lets up. Contact time is the step cut short most often.
A mess travels farther than crews expect, and a quick wipe leaves much of it behind. A professional decon spends its time on being thorough. It reaches every touched surface and gives the product the time it needs.
Maybe your target for getting a unit back cannot fit the contact time on the label. Then the answer is a different product, a spare unit, or a new target. It is never a shorter wet time.
Soft items and equipment
Each soft item gets a decision: clean it, launder it, or replace it. A cot mattress with a sound cover that resists fluid may be cleaned and disinfected like any hard surface. One with a torn cover, or with fluid that has soaked through the seams, usually has to be replaced. There is no reliable way to disinfect the foam under the cover.
Portable equipment is cleaned as its maker's instructions direct, with extra care for handles, cables, and buttons. Items like blood pressure cuffs and reusable straps are often missed in routine cleaning. They deserve careful attention during a full deep clean.
Tell the company ahead of time what it may throw out and replace on its own and what needs your approval. That saves you from surprises on the invoice and from delays in getting the unit back.
Oxygen cylinders, cylinder bags, and airway kits travel between units or sit in station storage. They are easy to forget. Ask the company to include them, or make sure your own staff clean them the same day. You do not want a freshly cleaned compartment restocked with items that were never cleaned.
Patrol cars and fire trucks
Ambulances get most of the attention. But patrol cars and fire trucks get soiled too. Think of a patrol car's rear compartment after carrying someone who was bleeding, vomiting, or incontinent. The seat, the partition, the floor, and the door handles all need attention. Hard plastic rear seats are easier to clean than cloth. But seams and seat belt latches still collect residue.
Fire truck cabs can be soiled by crews coming back in dirty gear after rescues at wrecks, medical calls, or fires. The air-pack seats, grab handles, and floor are the usual focus. The gear itself should go through your agency's gear-cleaning process. It should not be cleaned inside the cab.
The same rules apply to your whole fleet. Remove the heavy soil. Clean. Disinfect for the full label contact time. Write it down.
A decon after a transport, step by step
Here is a typical order of events, sketched as an illustration. An ambulance crew has just carried a patient with heavy bleeding on a long rural call. The cot, floor, bench seat, and one cabinet door are clearly soiled. The crew is not sure whether a used needle rolled under the cot during the ride.
The supervisor takes the unit out of service and asks the agency's contracted company for a full deep clean. The company's technician puts on protective gear and takes out the portable equipment to be cleaned on its own. The technician searches for needles and finds a capped syringe in a floor seam. The cot mattress cover is sound, so it is cleaned. The bench seat cushion has a split seam, so it is replaced from stock.
The technician cleans and disinfects every surface from ceiling to floor, keeping each area wet for the label contact time. After restocking, the supervisor and technician walk the unit together and sign the decon record. It lists the products, contact times, replaced items, and the syringe found. The unit goes back in service with the record in its file.
What the decon record includes
A decon record is your proof that the unit was handled properly. It backs up your infection control program and your audits. It also helps you answer questions from crew members or patients later.
Store your records where both your infection control officer and your fleet manager can find them. Ask your medical director whether your EMS license or local laws set any record rules.
- Unit number, date, and the times it went out of service and came back
- The event or reason that set off the decon
- Products used, EPA registration numbers, and contact times
- Soft items and equipment cleaned, laundered, or replaced
- Needles or unusual items found
- Name of the technician and of the supervisor who approved the return to service
Returning the unit to service
Putting your unit back in service should be a clear step, not something people assume. After restocking, a supervisor or a named crew member should look over the compartment. They should confirm that the equipment is back and working, and then sign the record.
Only then should you tell dispatch that the unit is available. That brief last check protects your next crew and your next patient.
After handback: repairs and crew feedback
Something found during decon may point to a wider issue. It could be a damaged cabinet seal, a cot mount that traps fluid, or a stain that keeps coming back in the same floor seam. A good company will note it in the record. Pass those notes to your fleet manager. Small repairs made quickly can keep the same problem from coming back in the next deep clean.
Last, go back to the crew who brought the unit in. Tell them it was cleaned, what was replaced, and whether a needle was found. That builds good habits. It also shows your crews that you take exposures seriously.